| Size | Price | |
|---|---|---|
| 2mg | ||
| 5mg | ||
| 10mg | ||
| 25mg | ||
| 50mg | ||
| Other Sizes |


Purity: ≥98%
| Targets |
NOP Receptor/ORL1
Cebranopadol acts as a potent agonist at the NOP receptor (ORL-1) and also exhibits agonist activity at the μ-opioid, δ-opioid, and κ-opioid receptors. |
|---|---|
| ln Vitro |
Cebranopadol (also known as GRT-6005) is a newly developed, first-in-class drug that exhibits strong agonist activity on both the well-established mu opioid receptor and ORL-1 (an opioid receptor similar to -1). The analgesic nociceptin/orphanin FQ peptide (NOP) cebranopadol has ED50 values of 0.5-5.6 µg/kg after intravenous and 25.1 µg/kg after oral administration. It has demonstrated high potency and efficacy in several rat models of acute and chronic pain (tail-flick, rheumatoid arthritis, bone cancer, spinal nerve ligation, diabetic neuropathy). Clinical trials in phases two and three are currently assessing its efficacy in treating both acute and chronic pain. Based on recent research, opioid and NOP receptor agonism may be used in conjunction as a novel treatment approach for cocaine addiction.
This specific (1α,4α) stereoisomer exhibits lower activity compared to the parent cebranopadol. The parent compound cebranopadol is a potent activator of the NOP receptor (ORL-1). The stereoisomer's in vitro activity profile is characterized by its receptor binding affinity and functional agonist potency at the NOP and opioid receptors, though specific numerical data for this stereoisomer are not detailed in the available literature. |
| ln Vivo |
Behavioral studies in pain models and pharmacokinetic evaluations were carried out in Sprague-Dawley rats (weight range 134−423 g); Iffa Credo, Brussels, Belgium provided the tail-flick model; Harlan Laboratories, Indianapolis, IN provided the bone cancer model; Janvier Laboratories, Le Genest Saint Isle, France provided the other pain models and pharmacokinetics); male rats were used in the majority of the experiments, with the exception of the bone cancer and tail-flick models, which used female Sprague-Dawley rats. Male Wistar rats, weighing between 150 and 375 grams, were used in side effect model studies (Depré, Saint Doulchard, France). The rats were kept in standard housing (20–24°C, 12 hours of light and dark, 35–70% relative air humidity, 10–15 air changes per hour, air movement<0.2 m/s), with unlimited access to food and water in their home cage. Except for mononeuropathy models, which required animals to undergo repeated testing with a minimum one-week washout period in between, all in vivo models only employed animals once. With the few exceptions listed below, animal testing was carried out in compliance with German Animal Welfare Law, the International Association for the Study of Pain's guidelines, and recommendations. The local government's animal research committee, which gets advice from a separate ethics committee, approved all study protocols. The treatment groups were assigned to the animals at random. Randomized tests were conducted using various doses and vehicles. The operators conducting the behavioral tests were unaware of the study hypothesis and the nature of drug differences, even though they were not formally "blinded" with regard to the treatment.
Cebranopadol demonstrates potent agonist activity at NOP and opioid receptors in vivo, producing significant analgesic effects in preclinical pain models. The parent compound shows efficacy in various models of acute and chronic pain. The specific (1α,4α) stereoisomer, being less active, would be expected to show reduced in vivo efficacy compared to the parent compound. |
| Enzyme Assay |
Cebranopadol (trans-6'-fluoro-4',9'-dihydro-N,N-dimethyl-4-phenyl-spiro[cyclohexane-1,1'(3'H)-pyrano[3,4-b]indol]-4-amine) is a novel analgesic nociceptin/orphanin FQ peptide (NOP) and opioid receptor agonist [Ki (nM)/EC50 (nM)/relative efficacy (%): human NOP receptor 0.9/13.0/89; human mu-opioid peptide (MOP) receptor 0.7/1.2/104; human kappa-opioid peptide receptor 2.6/17/67; human delta-opioid peptide receptor 18/110/105].[1]
Human MOP, DOP, KOP, and NOP receptor binding assays were run in microtiter plates with wheat germ agglutinin-coated scintillation proximity assay beads. [N-allyl-2,3-3H]naloxone and [tyrosyl-3,5-3H]deltorphin II, [3H]Ci-977, and [leucyl-3H]nociceptin were used as ligands for the MOP, DOP, KOP, and NOP receptor binding studies, respectively. The KD values of the radioligands used for the calculation of Ki values were provided as supplemental information. The assay buffer used for the MOP, DOP, and KOP receptor binding studies was 50 mM Tris-HCl (pH 7.4) supplemented with 0.052 mg/mL bovine serum albumin. For the NOP receptor binding studies, the assay buffer used was 50 mM HEPES, 10 mM MgCl2, 1 mM EDTA (pH 7.4). The final assay volume of 250 μL/well included 1 nM [3H]naloxone, 1 nM [3H]deltorphin II, 1 nM [3H]Ci-977, or 0.5 nM [3H]nociceptin as a ligand and cebranopadol in dilution series. Cebranopadol was diluted with 25% DMSO in water to yield a final 0.5% DMSO concentration, which also served as a respective vehicle control. Assays were started by the addition of beads (1 mg beads/well), which had been preloaded for 15 minutes at room temperature with 23.4 μg of human MOP membranes, 12.5 μg of human DOP membrane, 45 μg of human KOP membranes, or 25.4 µg of human NOP membranes per 250 µL of final assay volume. After short mixing, the assays were run for 90 minutes at room temperature. The microtiter plates were then centrifuged for 20 minutes at 500 rpm, and the signal rate was measured by means of a 1450 MicroBeta Trilux. IC50 values reflecting 50% displacement of [3H]naloxone-, [3H]deltorphin II-, [3H]Ci-977-, or [3H]nociceptin-specific receptor binding were calculated by nonlinear regression analysis. Individual experiments were run in duplicate and were repeated three times in independent experiments[1]. Radioligand binding assays using membrane preparations from cells expressing recombinant NOP or opioid receptors (μ, δ, κ), incubated with varying concentrations of the compound and a labeled reference agonist, to determine receptor binding affinity (Ki). The assays are typically performed using standard protocols for GPCR binding studies. |
| Cell Assay |
Cebranopadol was tested for its agonistic activity on human recombinant MOP, DOP, or NOP receptor-expressing cell membranes from Chinese hamster ovary K1 cells, or KOP receptor-expressing cell membranes from human embryonic kidney cell line 293 cells. For each assay, 10 µg of membrane proteins was incubated for 45 minutes at 25°C with 0.4 nM [35S]GTPγS (GE Healthcare) and various concentrations of agonists in a buffer containing 20 mM HEPES (pH 7.4), 100 mM NaCl, 10 mM MgCl2, 1 mM EDTA, 1 mM dithiothreitol, 1.28 mM NaN3, and 10 µM guanosine diphosphate. The bound radioactivity was calculated using the methods previously mentioned.
Functional assays measuring receptor-mediated signaling, such as [35S]GTPγS binding or cAMP inhibition, in cells expressing the target receptors to evaluate agonist potency (EC50) and efficacy. Cells are treated with varying concentrations of the compound, and the receptor-mediated response is measured to determine the compound's ability to activate the NOP and opioid receptor signaling pathways. |
| Animal Protocol |
8.9 and 26.6 mg/kg s.c. for whole-body plethysmography test in conscious rats. Sprague-Dawley ratsCebranopadol was dissolved in vehicle that consisted of 5% dimethylsulfoxide, 5% Emulphor, and 90% distilled water. The solution was vortexed before filling a 1-ml syringe for oral injection. Cebranopadol was injected orally by gavage at doses of 0.0, 25, and 50 μg/kg. Cocaine HCl was dissolved in 0.9% saline at a dose of 0.5 mg/kg/infusion and self-administered intravenously. Sweetened condensed milk was diluted 2:1 (v/v) in water.[2]
Effect of Cebranopadol on the Escalation of Cocaine Self-Administration[2] Rats (n = 14) were trained to self-administer cocaine under a fixed-ratio 1 (FR1) schedule of reinforcement in daily 6-hour sessions. Each active lever press resulted in the delivery of one cocaine dose (0.5 mg/kg/0.1 ml infusion). A 20-second timeout (TO) period followed each cocaine infusion. During the timeout period, responses on the active lever did not have scheduled consequences. This TO period occurred concurrently with illumination of a cue light that was located above the active lever to signal delivery of the positive reinforcement. The rats were trained to self-administer cocaine in 15 sessions (5 days/week) until a stable baseline of reinforcement was achieved (<10% variation over the last three sessions). A within-subjects Latin-square design was used for the drug treatments. The rats were orally injected with cebranopadol (0, 25, and 50 μg/kg) 30 minutes before beginning the sessions. Oral administration was performed by gavage using a 19-gauge needle and 8 cm of Tygon tubing (0.030 inch inner diameter, 0.090 inch outer diameter). The animals were subjected to cocaine self-administration at 2-day intervals between drug tests. Effect of Cebranopadol on Sweetened Condensed Milk Self-Administration[2] Rats (n = 12) were trained to self-administer SCM under an FR1 schedule of reinforcement for 6 hours per day to match cocaine self-administration. After each SCM reward delivery, a 20-second TO period occurred, during which responses on the active lever had no scheduled consequences. This TO period occurred concurrently with illumination of a cue light that was located above the active lever to signal delivery of the positive reinforcement. The rats were trained to self-administer SCM for several days until a stable baseline of reinforcement was achieved (<10% variation over the last three sessions). When the stable baseline was reached, the rats orally received cebranopadol (0, 25, and 50 μg/kg) 30 minutes before beginning the next session. The animals were subjected to SCM self-administration at 2-day intervals between drug tests. Cebranopadol-Induced Conditioned Place Preference and Locomotor Activity[2] Cebranopadol-induced CPP was evaluated using a biased, counterbalanced CPP procedure. Naive rats (n = 9) were handled and habituated to oral administration for 1 week before beginning the study. The experiment consisted of three 30-minute phases: pretest (one session), conditioning (eight sessions), and preference test (one session). The rats were placed in a dim (40 lux) room 30 minutes before starting the tests. A two-chambered (38 cm × 32 cm × 32 cm) place conditioning apparatus was used, with visual cues on the walls (stripes or dots for compartments A and B, respectively) and tactile cues on the floor (smooth or rough for compartments A and B, respectively). On day 1 (pretest), naive rats were placed between the two chambers and allowed to freely explore both chambers for 30 minutes. Individual bias toward either compartment A or B was observed, and the animals were assigned to place conditioning subgroups according to their least-preferred compartment; therefore, biased assignment was used. Conditioning was performed within subjects. Each rat received cebranopadol (25 μg/kg orally) and vehicle on alternating days in a counterbalanced design 30 minutes before being placed in the conditioning chamber. The preference test was performed 24 hours after the last conditioning session. Thirty minutes after vehicle administration, the rats were placed in the nonconditioned side of the apparatus with free access to both chambers. The time spent in the different chambers was recorded. Locomotor activity was recorded in each phase (pretest, conditioning, and preference test) using a video camera that was connected to the ANY-maze Video Tracking System 5.11. Effect of Cebranopadol on Conditioned Reinstatement of Cocaine-seeking Behavior[2] Cocaine Self-Administration Training.[2] Rats (n = 10) were surgically prepared with indwelling microurethane catheters that were inserted in the right jugular vein. After 7 days of postsurgical recovery, the rats began self-administration training. The rats were trained to self-administer cocaine (0.5 mg/kg/0.1 ml infusion, i.v.) for 6 hours/day on an FR1 schedule in the presence of a contextual/discriminative stimulus (SD). Each session was initiated by extending two retractable levers into the operant conditioning chamber. Constant 70-dB white noise served as a discriminative stimulus that signaled availability of the reinforcer throughout the session. Responses on the right, active lever were reinforced with a dose of cocaine, followed by a 20-second TO period that was signaled by illumination of a cue light above the active lever. During this TO period, the lever remained inactive to prevent accidental overdosing with cocaine. Responses on the left, inactive lever had no scheduled consequences. Conditioned Reinstatement.[2] Two days later, the rats were presented with the SD. To evaluate the effect of cebranopadol on the conditioned reinstatement of cocaine seeking, the rats were treated with cebranopadol (0, 25, and 50 μg/kg) in a counterbalanced Latin-square design 30 minutes before the reinstatement test. The reinstatement test lasted 2 hours under SD conditions, except that cocaine was unavailable. Cebranopadol was administered only in the SD conditions, with a 2-day interval between tests. Standard rodent models of pain (e.g., tail-flick, hot plate, or formalin test) administered with the compound via appropriate routes (oral, intravenous, or subcutaneous) to evaluate analgesic efficacy and dose-response relationships. The analgesic effect is typically measured as the latency to response (e.g., tail withdrawal) or the reduction in pain-related behaviors. |
| References | |
| Additional Infomation |
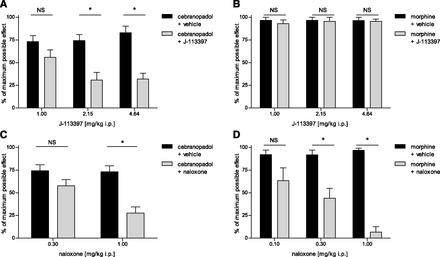
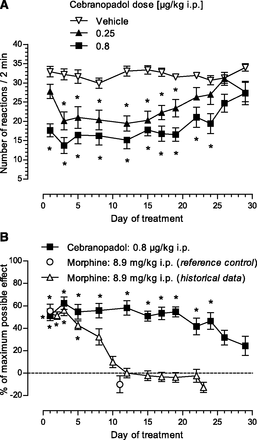
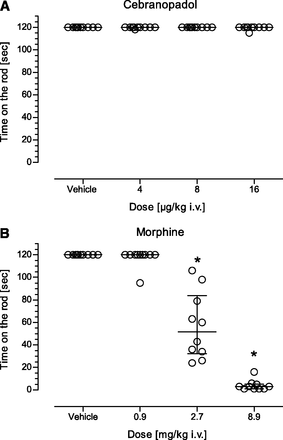
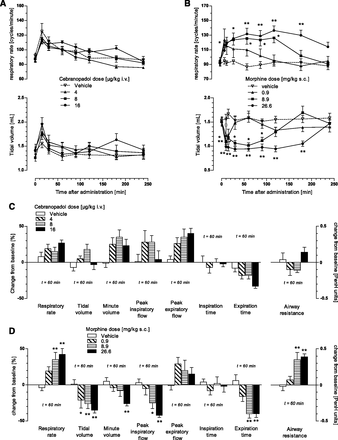
Sebranopado belongs to the indole class of compounds. Sebranopado has been used in clinical trials for the treatment of pain, cancer, and chronic pain. Sebranopado is an orally effective benzene compound that acts as an opioid peptide receptor agonist for nociceptors/orphanone FQ receptors (opioid receptor-like 1; OPRL1; ORL-1; NOP; κ-type 3 opioid receptors) and classical opioid receptors (μ, δ, and κ), possessing potential anti-nociceptive activity. After oral administration, serbranopado binds to NOP and μ, δ, and κ opioid receptors, enhancing NOP and opioid receptor-mediated signaling, interfering with pain sensation, thereby producing an analgesic effect. NOP is a member of the opioid receptor family, and its endogenous ligand, nociceptin, plays a crucial role in regulating various brain activities, including pain, as well as some inflammatory and immune responses. Drug Indications: Treatment of chronic pain. Cebranopadol (trans-6'-fluoro-4',9'-dihydro-N,N-dimethyl-4-phenyl-spiro[cyclohexane-1,1'(3'H)-pyrano[3,4-b]indole]-4-amine) is a novel analgesic belonging to the nociceptin/orphanone FQ peptide (NOP) and opioid receptor agonist class. [Ki (nM)/EC50 (nM)/Relative efficacy (%): human NOP receptor 0.9/13.0/89; human μ-opioid peptide (MOP) receptor 0.7/1.2/104; Cebranopadol has affinity for human κ-opioid peptide receptor 2.6/17/67 and human δ-opioid peptide receptor 18/110/105.] In various rat models of acute and chronic pain (tail-flick test, rheumatoid arthritis, bone cancer, spinal nerve ligation, and diabetic neuropathy), serbranopado demonstrated potent analgesic and anti-hyperalgesic effects, with an ED50 of 0.5–5.6 µg/kg after intravenous injection and 25.1 µg/kg after oral administration. Compared with selective MOP receptor agonists, serbranopado was more potent in chronic neuropathic pain models than in acute nociceptive pain models. The duration of action of serbranopado was long (up to 7 hours after intravenous injection of 12 µg/kg; and over 9 hours after oral administration of 55 µg/kg in the rat tail-flick test). In a spinal nerve ligation model, the analgesic activity of cebranopadol was partially reversed by pretreatment with the selective NOP receptor antagonist J-113397 [1-[(3R,4R)-1-cyclooctylmethyl-3-hydroxymethyl-4-piperidinyl]-3-ethyl-1,3-dihydro-2H-benzimidazole-2-one] or the opioid receptor antagonist naloxone, indicating that both NOP receptor and opioid receptor agonists are involved in this activity. In a chronic compression injury model, the development of analgesic tolerance to cebranopadol was significantly delayed compared to an equivalent analgesic dose of morphine (complete tolerance was achieved on days 26 and 11, respectively). Unlike morphine, cebranopadol did not interfere with motor coordination or respiration at doses within and above the analgesic dose range. Cebranopadol is a novel nociceptin/orphanone q (NOP) and opioid receptor agonist with analgesic effects, showing high analgesic efficacy in various pain models with minimal side effects. [1] Cebranopadol is currently undergoing phase II and III clinical trials for the treatment of chronic and acute pain. Recent evidence suggests that the combined action of opioid receptor and NOP receptor agonists may be a novel strategy for treating cocaine addiction. To further investigate these findings, we investigated the effects of Cebranopadol on cocaine self-administration (0.5 mg/kg/time) and conditioned relapse in rats with long-term cocaine exposure. Oral administration of sibranopaldo (0, 25, and 50 μg/kg) reversed the increase in cocaine self-administration after long-term (6-hour) free cocaine intake in rats, but had no effect on self-administration of sweetened condensed milk (SCM). Sebranopadol induced conditioned position preference but did not affect motor activity during conditioned reflex training. In addition, sibranopado blocked relapse of conditioned cocaine cravings. These results suggest that oral sibranopado prevents addiction-like behaviors (i.e., increased intake and relapse), suggesting it may be a novel strategy for treating cocaine use disorder. However, the conditioned position preference observed after sibranopado administration suggests that the compound may have some intrinsic reward effect. [2]
A limitation of this study is the lack of a comprehensive characterization of the pharmacokinetics and pharmacodynamics of sibranopado. We also did not assess the effect of sibranopado on the pharmacokinetics of cocaine. However, we considered the reduction in cocaine dose escalation to be unrelated to the possible pharmacokinetic effects of cocaine levels in the blood, as sibranopado effectively reduced conditioned relapse. In this study, its potential effect on cocaine levels in the blood was excluded due to the unavailability of cocaine. We also did not find any shift in the dose-response curve or specific receptors mediating its preclinical efficacy. Further research is needed to fully characterize the intensifying properties and potential abuse risks of sbranopado, especially given that we found that sbranopado can induce conditioned place preference. However, although such characterization studies are theoretically crucial for understanding the exact mechanism of action of the drug and for advancing drug development, sbranopado has been shown to be well-tolerated in humans and is currently being tested for pain management in several clinical trials. In summary, this study provides preclinical evidence of the efficacy of sbranopado in reversing cocaine compulsion-like responses and cue-induced cocaine craving relapse. Sebranopado may be a novel treatment option for preventing cocaine abuse and relapse. [2] |
| Molecular Formula |
C24H27FN2O
|
|---|---|
| Molecular Weight |
378.482389688492
|
| Exact Mass |
378.21
|
| Elemental Analysis |
C, 68.34; H, 6.58; F, 4.00; N, 5.90; O, 15.17
|
| CAS # |
863513-93-3
|
| Related CAS # |
Cebranopadol; 863513-91-1
|
| PubChem CID |
11848225
|
| Appearance |
White to gray solid powder
|
| LogP |
4.3
|
| Hydrogen Bond Donor Count |
1
|
| Hydrogen Bond Acceptor Count |
3
|
| Rotatable Bond Count |
2
|
| Heavy Atom Count |
28
|
| Complexity |
553
|
| Defined Atom Stereocenter Count |
0
|
| SMILES |
N([C@@]1(CC[C@]2(OCCC3C4C=C(F)C=CC=4NC2=3)CC1)C1C=CC=CC=1)(C)C
|
| InChi Key |
CSMVOZKEWSOFER-UHFFFAOYSA-N
|
| InChi Code |
InChI=1S/C24H27FN2O/c1-27(2)23(17-6-4-3-5-7-17)11-13-24(14-12-23)22-19(10-15-28-24)20-16-18(25)8-9-21(20)26-22/h3-9,16,26H,10-15H2,1-2H3
|
| Chemical Name |
6-fluoro-N,N-dimethyl-1'-phenylspiro[4,9-dihydro-3H-pyrano[3,4-b]indole-1,4'-cyclohexane]-1'-amine
|
| Synonyms |
GRT6005; GRT 6005; GRT-6005; Cebranopadol
|
| HS Tariff Code |
2934.99.9001
|
| Storage |
Powder -20°C 3 years 4°C 2 years In solvent -80°C 6 months -20°C 1 month |
| Shipping Condition |
Room temperature (This product is stable at ambient temperature for a few days during ordinary shipping and time spent in Customs)
|
| Solubility (In Vitro) |
DMSO: 10mM
Water: 1 mg/mL (Insoluble) Ethanol: |
|---|---|
| Solubility (In Vivo) |
Note: Listed below are some common formulations that may be used to formulate products with low water solubility (e.g. < 1 mg/mL), you may test these formulations using a minute amount of products to avoid loss of samples.
Injection Formulations
Injection Formulation 1: DMSO : Tween 80: Saline = 10 : 5 : 85 (i.e. 100 μL DMSO stock solution → 50 μL Tween 80 → 850 μL Saline)(e.g. IP/IV/IM/SC) *Preparation of saline: Dissolve 0.9 g of sodium chloride in 100 mL ddH ₂ O to obtain a clear solution. Injection Formulation 2: DMSO : PEG300 :Tween 80 : Saline = 10 : 40 : 5 : 45 (i.e. 100 μL DMSO → 400 μLPEG300 → 50 μL Tween 80 → 450 μL Saline) Injection Formulation 3: DMSO : Corn oil = 10 : 90 (i.e. 100 μL DMSO → 900 μL Corn oil) Example: Take the Injection Formulation 3 (DMSO : Corn oil = 10 : 90) as an example, if 1 mL of 2.5 mg/mL working solution is to be prepared, you can take 100 μL 25 mg/mL DMSO stock solution and add to 900 μL corn oil, mix well to obtain a clear or suspension solution (2.5 mg/mL, ready for use in animals). View More
Injection Formulation 4: DMSO : 20% SBE-β-CD in saline = 10 : 90 [i.e. 100 μL DMSO → 900 μL (20% SBE-β-CD in saline)] Oral Formulations
Oral Formulation 1: Suspend in 0.5% CMC Na (carboxymethylcellulose sodium) Oral Formulation 2: Suspend in 0.5% Carboxymethyl cellulose Example: Take the Oral Formulation 1 (Suspend in 0.5% CMC Na) as an example, if 100 mL of 2.5 mg/mL working solution is to be prepared, you can first prepare 0.5% CMC Na solution by measuring 0.5 g CMC Na and dissolve it in 100 mL ddH2O to obtain a clear solution; then add 250 mg of the product to 100 mL 0.5% CMC Na solution, to make the suspension solution (2.5 mg/mL, ready for use in animals). View More
Oral Formulation 3: Dissolved in PEG400 (Please use freshly prepared in vivo formulations for optimal results.) |
| Preparing Stock Solutions | 1 mg | 5 mg | 10 mg | |
| 1 mM | 2.6421 mL | 13.2107 mL | 26.4215 mL | |
| 5 mM | 0.5284 mL | 2.6421 mL | 5.2843 mL | |
| 10 mM | 0.2642 mL | 1.3211 mL | 2.6421 mL |
*Note: Please select an appropriate solvent for the preparation of stock solution based on your experiment needs. For most products, DMSO can be used for preparing stock solutions (e.g. 5 mM, 10 mM, or 20 mM concentration); some products with high aqueous solubility may be dissolved in water directly. Solubility information is available at the above Solubility Data section. Once the stock solution is prepared, aliquot it to routine usage volumes and store at -20°C or -80°C. Avoid repeated freeze and thaw cycles.
Calculation results
Working concentration: mg/mL;
Method for preparing DMSO stock solution: mg drug pre-dissolved in μL DMSO (stock solution concentration mg/mL). Please contact us first if the concentration exceeds the DMSO solubility of the batch of drug.
Method for preparing in vivo formulation::Take μL DMSO stock solution, next add μL PEG300, mix and clarify, next addμL Tween 80, mix and clarify, next add μL ddH2O,mix and clarify.
(1) Please be sure that the solution is clear before the addition of next solvent. Dissolution methods like vortex, ultrasound or warming and heat may be used to aid dissolving.
(2) Be sure to add the solvent(s) in order.
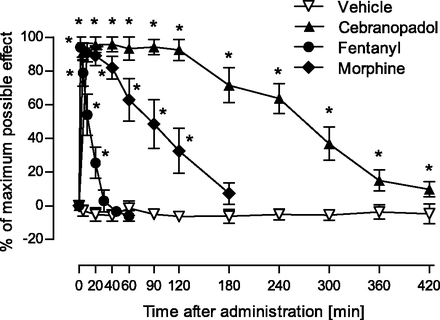
Duration of action of cebranopadol (12µg/kg) compared with fentanyl (9.4µg/kg) and morphine (1.9 mg/kg) after intravenous administration in the rat tail-flick test.J Pharmacol Exp Ther.2014 Jun;349(3):535-48. |
|---|
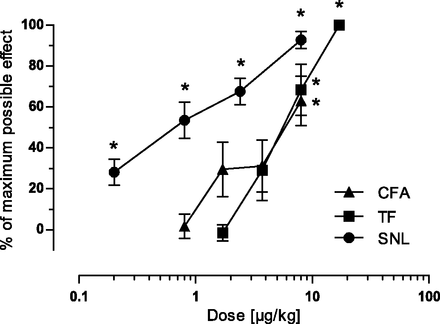
Analgesic effect of cebranopadol on spinal nerve ligation-induced mononeuropathic pain (SNL) and complete Freund’s adjuvant-induced chronic rheumatoid arthritic pain (CFA) 30 minutes after, and on tail flick-induced heat nociception (TF) 20 minutes after intravenous administration.J Pharmacol Exp Ther.2014 Jun;349(3):535-48. |
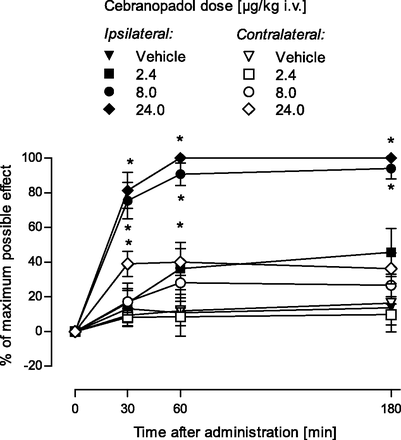
Effect of intravenous cebranopadol on mechanical sensitivity in the ipsilateral and contralateral paws in a rat model of bone cancer pain.J Pharmacol Exp Ther.2014 Jun;349(3):535-48. |
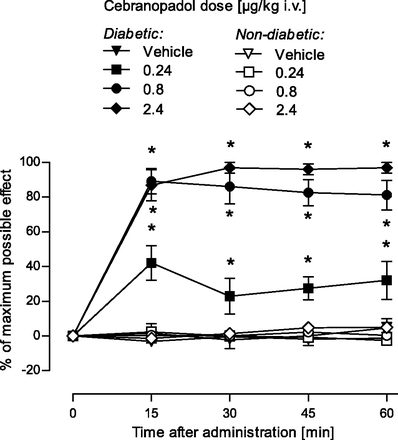
Antihyperalgesic activity of cebranopadol in streptozotocin (STZ)-treated and control rats measured as % MPE (mean ± S.E.M.;n= 10) by means of a paw pressure test in a model of STZ-induced diabetic polyneuropathy.J Pharmacol Exp Ther.2014 Jun;349(3):535-48. |
|---|
Effect of 1.0, 2.15, and 4.64 mg/kg i.p. J-113397 on the antihypersensitive effect of 1.7μg/kg i.v. cebranopadol (A) and 8.9 mg/kg i.v. morphine (B) in the spinal nerve ligation (SNL) model. Effect of 0.3 and 1.0 mg/kg i.p. naloxone on the antihypersensitive effect of 1.7μg/kg i.v. cebranopadol (C) and of 0.1, 0.3, and 1.0 mg/kg i.p.naloxone on the antihypersensitive effect of 8.9 mg/kg i.v. morphine (D) in the SNL model. Data are given as percentage of maximum possible effect (mean ± S.E.M.;n= 10) measured with an electronic von Frey filament based on the measurement of ipsilateral withdrawal thresholds 30 minutes after administration of cebranopadol or morphine.J Pharmacol Exp Ther.2014 Jun;349(3):535-48. |
Antiallodynic effect of repeated daily intraperitoneal administration of cebranopadol or vehicle as measured by number of paw lifts from a cold plate during 2 minutes (mean ± S.E.M.;n= 13–15) (A) or % MPE (B) in the chronic constriction injury model.J Pharmacol Exp Ther.2014 Jun;349(3):535-48. |
Dose-dependent effects of cebranopadol (A) and morphine (B) on motor coordination in rats.J Pharmacol Exp Ther.2014 Jun;349(3):535-48. |
|---|
Effects of cebranopadol (A and C) and morphine (B and D) on respiratory function in the whole-body plethysmography test in conscious rats.J Pharmacol Exp Ther.2014 Jun;349(3):535-48. |
Products are for research use only; We do not sell to patients
Copyright 2020 InvivoChem LLC | All Rights Reserved


 COA